ICU Trials by ClinCalc

Screenshots

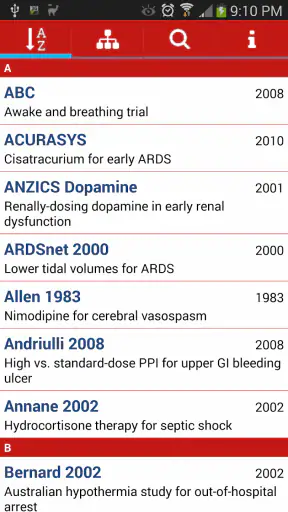
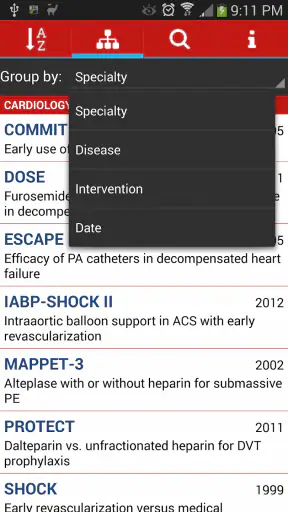

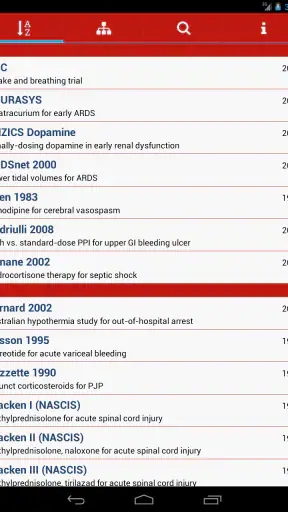
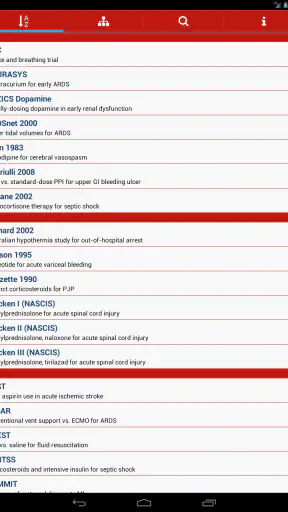
Details
- Rating
- 16.00 reviews
- Version
- 2026.07
- Developer
- ClinCalc LLC
Analysis by Norviv
When I first opened ICU Trials, I understood its appeal almost immediately: it turns a large body of critical-care research into something I could consult without opening a textbook or searching through scattered notes. Developed by ClinCalc LLC, this paid medical app is designed for clinicians, trainees, and serious learners who want landmark intensive-care trials close at hand. My first impression was practical rather than flashy, and that is exactly the point. It is a reference tool, not a course, simulator, or patient-facing health app.
The app costs $4.99, carries an Everyone age rating, and has built a small but clearly interested audience, with a 4.6 average from more than two hundred ratings and over ten thousand installs. Those figures suggest a focused medical utility rather than a mass-market download. After spending time with it, I think that description fits: its value depends less on how often you browse it casually and more on whether critical-care evidence is part of your regular study or clinical routine.
What makes the first week useful
The strongest early experience comes from discovering how quickly a question can become a focused review session. Instead of beginning with a broad web search, I can use the app as a starting point when I want to recall what a major intensive-care trial examined and why it matters. That change in workflow is more important than it sounds. Search engines often return guidelines, commentary, advertisements, and unrelated papers before I reach the original evidence. A compact trial reference reduces that initial friction.
I found the app most useful when I approached it with a specific purpose. For example, before discussing a management choice with a colleague, I could use a trial summary to refresh the patient population, intervention, comparison, and general conclusion. That is a better use of the app than opening it with the vague hope of “learning critical care” in a few minutes. It supports targeted recall; it does not replace a structured curriculum.
A realistic everyday scenario would be a resident preparing for an ICU teaching round. The night before, the resident could review several relevant landmark studies, note which questions each trial addressed, and then follow up with the full publication or current guideline. During a busy shift, the app can serve as a memory prompt. It is especially helpful when the name of a trial is familiar but its practical implication has become blurred after months away from the topic.
That distinction is central to using it responsibly. A summary can help me remember the shape of evidence, but it is not the same as reading methods, subgroup analyses, adverse outcomes, or later studies. I would not use a short entry as the sole basis for a high-stakes decision. The sensible workflow is to use the app for orientation, then verify important details in the original paper, a current guideline, or a trusted institutional resource.
During the first week, I would recommend building a personal routine around questions rather than browsing every entry in order. Start with conditions or interventions you encounter most often. After reading a summary, ask what population was studied, whether the result applies to the patient in front of you, and what later evidence might have changed the interpretation. That turns a passive reference session into active learning.
Stories Picked for You

Life360 Works Better When Your Household Agrees on What to Share

YouVersion Bible Fits Scripture into Everyday Phone Routines

Matchington Mansion Review: Match-Three Puzzles With a Place to Restore
Android Auto Shows Why Safer Driving Software Does Less
Google Find Hub Runs on Shared Devices and Quiet Trust

Sygic GPS Navigation: The Ultimate Offline Travel Companion
Where it fits beside ordinary alternatives
The usual alternatives are a general search engine, a medical textbook, a guideline app, or a collection of saved journal articles. Each has a different strength. Search is broader but noisier. Textbooks provide context and teaching structure but can take longer to navigate. Guidelines are better for current recommendations, while original papers offer the detail needed to judge reliability and applicability.
ICU Trials works best in the gap between memory and primary literature. It is faster than opening several papers and more focused than a general search, but it is not intended to replace either one. That makes its role unusually clear. I see it as a trial-recognition and revision tool: something that helps me identify the evidence worth reading next.
One non-obvious advantage of this role is that it can improve the quality of a later search. If I remember the broad question and design of a landmark study, I can search for follow-up research more intelligently. Rather than typing a vague clinical phrase, I can look for the original population, intervention, or outcome and then compare newer evidence. The app therefore has value beyond the minutes spent inside it, provided I treat each summary as a launch point.
Why the value can continue after the novelty fades
The first-week appeal is easy to understand, but a medical reference app earns its place through repeated use. After the initial exploration, the question becomes whether I will return to it when I am not deliberately testing it. In my experience, the answer depends on how closely my work or study schedule touches intensive care. For someone preparing for examinations, rotating through an ICU, or teaching acute-care concepts, the summaries can remain useful as compact revision prompts.
Month to month, the app is most valuable when attached to an existing habit. I could review one trial after a teaching session, revisit an entry before journal club, or use it to organize a study list for a particular clinical theme. These are small actions, but they give the app a recurring job. Without that habit, it risks becoming another medical reference installed with good intentions and opened only a few times.
I would not recommend trying to read everything repeatedly. That approach creates unnecessary fatigue and does not reflect how clinicians usually learn. A better method is to keep a rotating set of topics: perhaps one area related to current practice, one area connected to an upcoming assessment, and one area chosen because the evidence is frequently discussed. The app then becomes a lightweight review companion rather than an endless catalogue.
Another useful workflow is to pair each entry with one external action. After reading a summary, write one sentence about the clinical question, save the original article for later, or compare the conclusion with a current guideline. This prevents the common problem of recognizing a trial name without understanding its limitations. The app supplies a compact reminder; the follow-up activity supplies depth.
Its long-term value also depends on the reader’s expectations. If I want continuously updated recommendations, detailed dosing guidance, or a complete critical-care textbook, I would choose another resource. The app’s appeal is narrower and more durable when I value quick access to landmark evidence rather than a single platform that tries to cover every part of medical practice.
How much maintenance does it require?
The maintenance burden appears low in the everyday sense: there is no complicated study system I need to configure before using it, and the basic purpose is immediately understandable. That makes it easier to keep available for occasional reference. The current version is 2026.07, and the app has been available since June 9, 2012, which gives it the profile of an established reference rather than a brand-new experiment.
However, low app maintenance does not mean low professional responsibility. Medical evidence changes, and a landmark trial summary can become misleading if I forget to check whether later research, revised definitions, or updated recommendations have altered its practical meaning. I would maintain my own verification habit even when the app feels convenient. For high-stakes questions, the app should be the beginning of the check, not the final authority.
This is one of the most important trade-offs. A concise reference is easier to consult than a large database, but concision necessarily leaves out context. I may remember the headline result while overlooking exclusion criteria or whether the intervention was tested in a setting unlike my own. The app saves time at the retrieval stage, but I must spend time judging applicability when the decision matters.
The minimum operating requirement is Android 8.0, so it remains accessible to users who are not carrying the newest phone. That is a practical benefit for a reference app, because medical learners and staff may keep older devices as secondary tools. The $4.99 purchase also makes the decision straightforward: the cost is modest, but the app still needs to match a real recurring need. A low price does not make an unused reference valuable.
I would also consider the kind of device and setting in which I plan to use it. A phone is convenient for quick recall, but extended reading and comparison may be more comfortable on a larger screen or with a separate notebook. If my study style depends on highlighting long passages, building elaborate annotations, or managing full-text articles in one place, a dedicated reference manager or journal platform may serve me better.
Where repeated use can become tiring
The main source of fatigue is not a complicated interface; it is the nature of the material. Landmark critical-care trials can be dense, and summaries can begin to feel similar when I read several in one sitting. Interventions, outcomes, and conclusions blur together unless I actively compare them. The app is therefore better for short, purposeful sessions than for marathon browsing.
Another source of friction is the temptation to treat a summary as a conclusion without asking how strong the evidence really is. A quick entry can create confidence faster than understanding. I need to slow down when the patient population, intervention, or outcome differs from the case I am considering. This is not a flaw unique to the app, but its convenience makes the risk worth stating clearly.
There is also a motivational limit. The app can remind me what a trial was about, but it cannot replace a teacher, discussion, or deliberate practice. If I am studying for an examination, I still need questions and explanations. If I am preparing for clinical work, I still need guidelines and local protocols. If I am conducting research, I need the original methods and complete results. The app supports these activities but does not supply them.
For that reason, some readers should skip it. Patients and family members looking for understandable medical advice are unlikely to find a trial-summary reference appropriate. Beginners who need foundational physiology may be better served by a guided course or textbook. Clinicians who need current bedside recommendations more than historical evidence may prefer a guideline-focused tool. And anyone unwilling to verify important details should not rely on a condensed reference for decisions that carry meaningful risk.
On the other hand, the app is a strong fit for someone who already understands basic clinical language and wants a fast way to refresh major ICU evidence. It can also suit educators who need a prompt for discussion, provided they bring the full paper or a reliable guideline when the group needs detail. The best users are not those looking for a magic shortcut; they are people who know when a shortcut is useful and when it is unsafe.
Small habits that improve the experience
I would use a three-step check each time an entry influences my thinking. First, identify the exact clinical question. Second, ask whether the study population resembles the patient or scenario under discussion. Third, confirm the current recommendation elsewhere before acting. This takes little time and prevents the app’s speed from becoming false certainty.
I would also avoid reading summaries in alphabetical order simply because that feels organized. Grouping them around a rotation, an upcoming presentation, or a recurring clinical problem makes recall more durable. The app becomes more useful when I connect the trial to a decision rather than memorizing isolated names.
A third tactic is to explain the study aloud in plain language after reading it. If I cannot describe what was compared and what changed without looking back, I probably recognized the entry without learning it. This simple test exposes gaps that a quick reread might hide.
Finally, I would keep a separate note of questions the app raises. A summary that makes me wonder about an exclusion criterion, a later trial, or a conflicting guideline has done its job. That question list can guide deeper reading and journal-club preparation. In this way, the app’s limitations become useful prompts rather than disappointments.
Does it deserve lasting space?
My long-term verdict is positive, with a clear boundary around what I expect it to do. ICU Trials earns lasting space on my device if I regularly study or work with critical-care evidence and want a quick, focused reminder of landmark trials. Its greatest strength is not breadth for its own sake. It is the ability to shorten the distance between a clinical question and the evidence trail I should investigate.
It does not earn that space because it can replace textbooks, guidelines, or original research. It earns it because those resources are often easier to use after I have regained the basic shape of a trial. That makes the app particularly effective as a bridge: quick enough for a busy day, focused enough for revision, and useful as a prompt for deeper reading.
The audience size and 4.6 average rating indicate that it has found a receptive group, but I would not interpret that as a reason for everyone to buy it. Its value is specialized. The paid model is reasonable for a professional reference, yet the purchase makes most sense when I can name a recurring use case before installing it: ICU rotation review, exam preparation, teaching, or evidence-oriented clinical discussion.
After the novelty fades, the deciding factor is habit. If I open it only once to browse interesting trial names, it will probably become digital shelf decoration. If I use it for focused refreshers, follow each important entry with verification, and connect it to real questions from practice or study, it remains useful month after month.
In short, I recommend it to medically literate users who want a compact critical-care trial reference and understand its limits. I would choose a different tool for current guidelines, full-text research, patient education, or structured beginner learning. Used in its proper role, though, this app is a practical little companion: not the final word, but a reliable way to remember where the important conversation begins.
Frequently Asked Questions
01What is ICU Trials by ClinCalc used for?
ICU Trials by ClinCalc is an educational reference app designed for clinicians, students, and healthcare professionals who want quick access to summaries of important intensive care unit clinical trials. It helps users review study objectives, patient populations, interventions, outcomes, and key conclusions without searching through lengthy journal articles. The app is best viewed as a learning and decision-support reference, not as a replacement for current guidelines, institutional protocols, or professional judgment.
02Does ICU Trials by ClinCalc provide current medical advice or treatment recommendations?
The app summarizes published critical care evidence, but it should not be treated as a personalized medical advice tool or an automatically updated treatment protocol. Clinical evidence can change as new trials, systematic reviews, safety warnings, and guidelines become available. Before applying information to a patient, users should verify the original publication, check the date and context of the evidence, consider local policies, and consult an appropriately qualified clinician. Patient-specific decisions always require professional assessment.
03What topics and types of studies can I find in ICU Trials by ClinCalc?
The app focuses on landmark and clinically relevant trials from intensive care and emergency medicine. Depending on the available database and version, summaries may cover areas such as resuscitation, sepsis, mechanical ventilation, sedation, hemodynamics, renal replacement therapy, transfusion, nutrition, and other critical care interventions. Each entry is intended to make major studies easier to review, although the depth of information may differ between trials and a summary cannot replace reading the complete paper.
04Can ICU Trials by ClinCalc be used offline in the hospital or during study sessions?
The app is intended to provide convenient access to trial information on a mobile device, which can be useful during rounds, teaching, exam preparation, or personal study. Offline availability may depend on how the app stores its content and on the specific operating-system version. It is sensible to open the application after installation and test the required sections before relying on it in a location with limited connectivity. Users should also keep the app updated when new releases are available.
05Is ICU Trials by ClinCalc suitable for medical students and non-specialists?
Medical students, residents, pharmacists, nurses, and clinicians with an interest in critical care may find the app useful for building familiarity with major ICU evidence. However, some trial summaries use medical terminology and assume a basic understanding of study design, statistics, and intensive care practice. Beginners may need additional explanations from textbooks, courses, or supervisors. Non-specialists should avoid using the app to make independent treatment decisions, since interpreting trial results requires clinical context and appropriate training.


